
Obesity is a major global health burden, associated with an increased risk of type 2 diabetes, cardiovascular disease, and other metabolic disorders. In recent years, great success achieved by Semaglutide and Tirzepatide has attracted wide spread attention to due to their remarkable effects on weight loss and glycemic control, substantially enhancing the research interest and therapeutic potential of GLP-1 as well as other obesity-related targets.
GLP-1 and its mechanism of function
GLP-1 (Glucagon-like peptide-1) is an incretin secreted from intestinal L cells. GLP-1(7–37) and GLP-1(7–36) amide (Figure 1) are the two major bioactive forms of GLP-1 in vivo. GLP-1 activates the GLP-1 receptor (GLP-1R) in a glucose-dependent manner to potentiate insulin release and suppress glucagon secretion, and thereby lead to blood sugar lowering and weight loss [1].

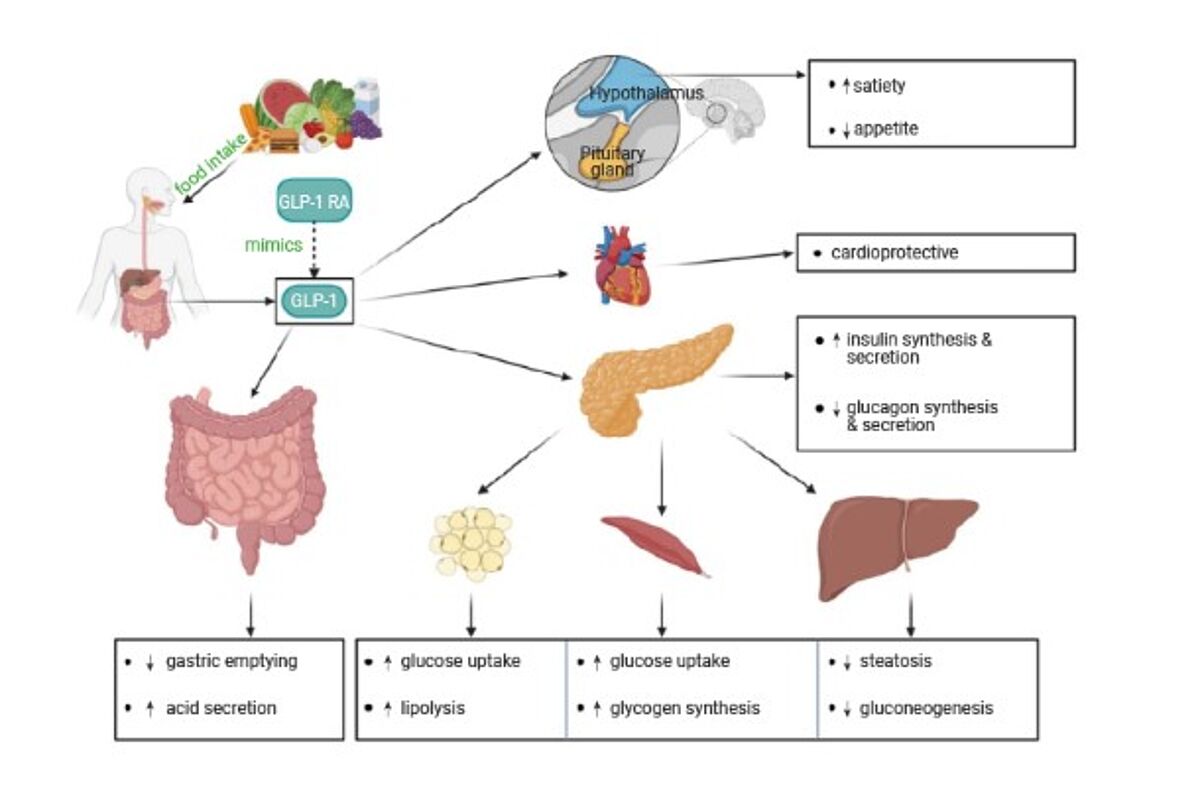
Nutrients intake can stimulate the secretion of GLP-1, which functions through binging to GLP-1R. This binding activates adenylate cyclase, leading to elevation of cAMP and PKA, which finally enhances insulin biosynthesis and secretion, and suppressed glucagon secretion [3]. Besides pancreas, GLP-1R also presents in kidney, heart, liver, etc. So GLP-1 exerts broad benefits like suppressing appetite, delaying gastric emptying, decreasing glucose production as well as lowering the risk of cardiovascular diseases (Figure 2) [3].
Other obesity-related targets
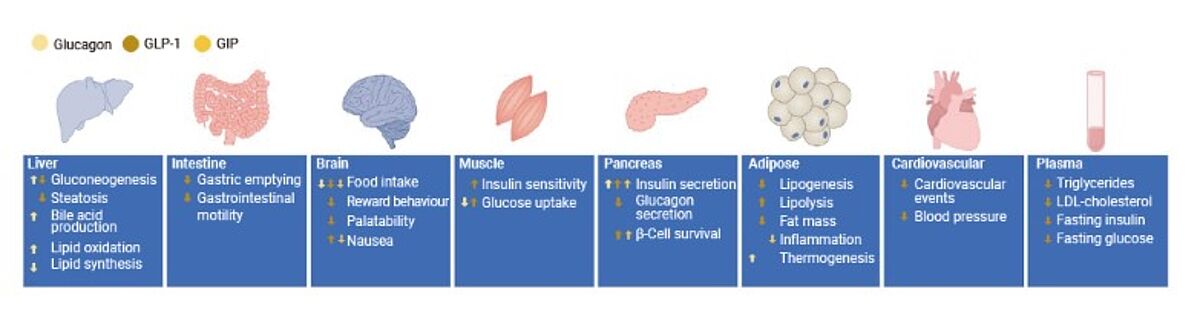
In addition to GLP-1R, targets such as GIPR, GCGR, and AMYR also play critical roles in metabolic regulation, gastrointestinal function, appetite control, and energy homeostasis, and have emerged as key therapeutic targets in obesity research in recent years.
GIPR
GIP (gastric inhibitory polypeptide) is an incretin secreted by intestinal K cells. By activating the glucose-dependent insulinotropic polypeptide receptor (GIPR), GIP stimulates glucose-dependent insulin secretion and regulates metabolic homeostasis [4].
GCCR
Glucagon (GCG) is secreted by pancreatic α-cells in response to hypoglycemia—seemingly counterproductive at least in a diabetes context. However, glucagon also promotes lipolysis, fatty acid oxidation, ketogenesis, thermogenesis, energy expenditure, bile acid synthesis, satiety, and appetite suppression, which makes glucagon receptor (GCGR) a promising target for weight control, if its hyperglycemic liability can be restrained [5].
AMYR
Amylin, also known as islet amyloid polypeptide (IAPP), is a member of the calcitonin peptide family. It is a 37-amino acid peptide expressed primarily by pancreatic islet β-cells and co-secreted with insulin, and signals through activation of the amylin receptors (AMYRs, CTR–RAMP complexes).
Circulating amylin is primarily secreted in response to nutrient intake or secretagogue stimulation. It reaches multiple peripheral organs, including the heart, skeletal muscle, liver, intestine, and brain, and primarily acts circumventricular organs of the brain, where it suppresses appetite, delays gastric emptying, enhances satiety, and reduces food intake. Thus, amylin contributes to the regulation of glucose homeostasis and energy metabolism [6].
MC4R
The melanocortin receptor 4 (MC4R) belongs to the melanocortin receptor family of GPCRs, which also includes MC1R, MC2R, MC3R, and MC5R. MC4R is predominantly expressed in the central nervous system and plays a critical role in the control of appetite and feeding behavior.
MC4R associated signaling pathways include leptin–melanocortin pathway, G protein–mediated signaling, β-arrestin signaling, and Ca²⁺-dependent pathways, all of which are closely linked to obesity and energy metabolism.
Case studies
GLP-1RAs and Obestiy
GLP-1RAs (GLP-1 receptor agonists) function through activating GLP-1R and are primarily used in the treatment of T2D (type 2 diabetes) and obesity.
In the 1980s, GLP-1 were found and scientists tried to design drugs based on the active forms of GLP-1—— GLP-1(7-37) and GLP-1(7-36) amide. However, natural GLP-1 is rapidly broken down by dipeptidyl peptidase 4 (DPP-4), making it unsuitable for clinical use.
Liraglutide
Liraglutide is the first approved GLP-1RA for obesity treatment, which is designed based on native GLP-1(7–37).
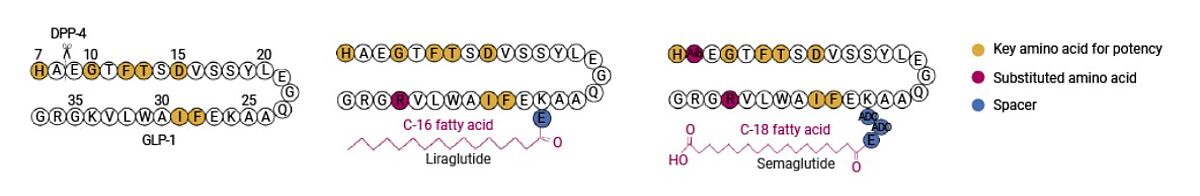
Liraglutide was engineered by conjugating a C16 saturated fatty acid (palmitic acid) to the side chain of Lys26 in GLP-1(7–37), thereby enhancing albumin binding. In addition, Lys34 was substituted with Arg to prevent nonspecific acylation at multiple Lys residues. These modifications prolong its plasma half-life to approximately 13 hours [7].
Semaglutide
Semaglutide has emerged as a landmark GLP-1RA, owing to its unprecedented weight-loss efficacy and remarkable commercial success in the anti-obesity drug market.
Semaglutide is also a long-acting GLP-1RA engineered from native GLP-1(7–37). Through multiple structural modifications, it markedly improves in vivo stability and prolongs its half-life while largely retaining high affinity for the GLP-1R.
In semaglutide, a C18 fatty diacid moiety is conjugated to the side chain of Lys26 via a hydrophilic linker, enabling reversible binding to plasma albumin and prolonged systemic exposure. In addition, Lys34 is substituted with Arg to prevent nonspecific acylation. And Ala8 is replaced with a non-natural amino acid Aib (α-aminoisobutyric acid), thereby markedly enhancing resistance to DPP-4-mediated degradation and extending the plasma half-life to approximately 7 days [7].
Orforglipron
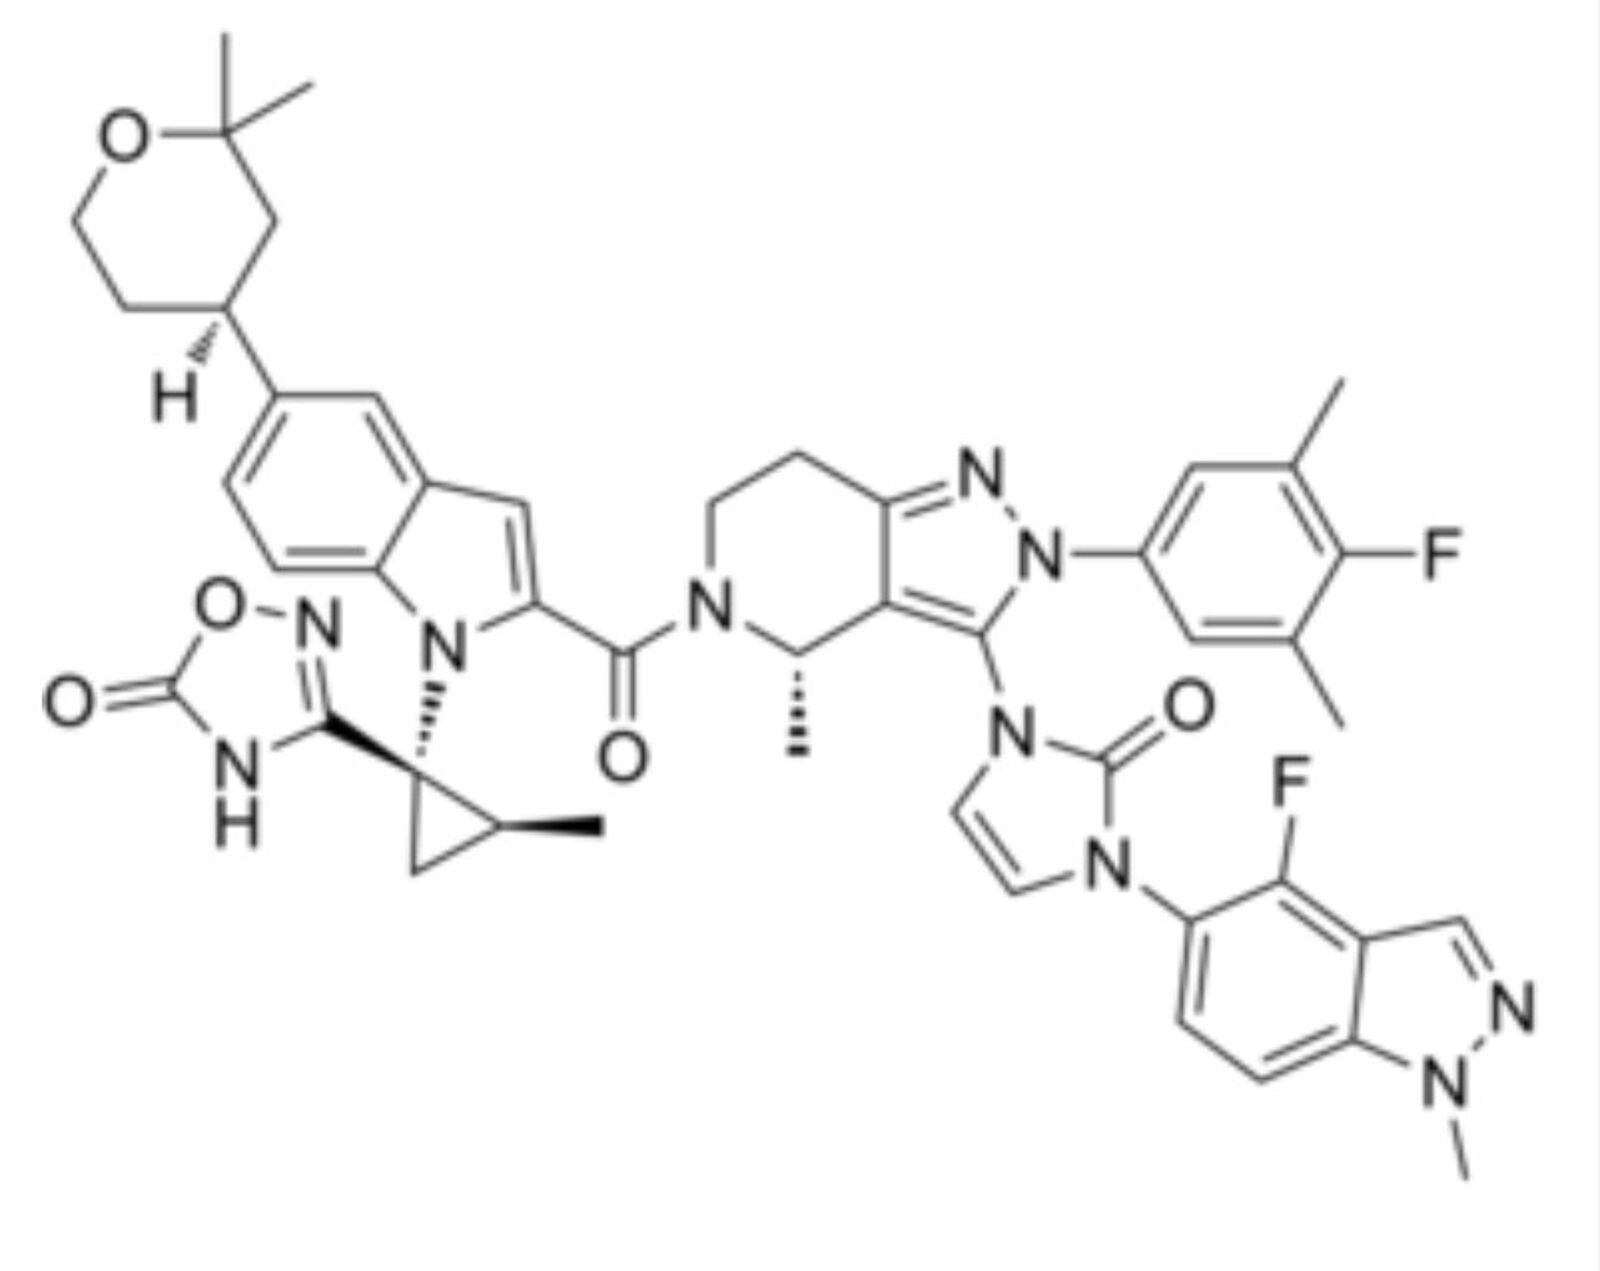
Orforglipron (LY3502970) is a non-peptide, small molecule oral GLP-1RA developed for weight management and T2D. Specifically, orforglipron is designed as a potent partial agonist of the GLP-1R that has a greater effect on cyclic AMP (cAMP) signaling than on β-arrestin recruitment. This biased agonism may offer lower receptor desensitization than full GLP-1 receptor agonists. Orforglipron has a half-life of 29-49 hours, supporting once-daily administration. Clinical trials indicate mild to moderate adverse events which were mostly gastrointestinal effects [8].
GLP-1 based multi-target agonists
With the maturation of single-target GLP-1 peptide therapeutics, the development of dual- and multi-receptor agonists targeting related gastrointestinal hormone receptors has emerged as a promising therapeutic research direction.
Tirzepatide
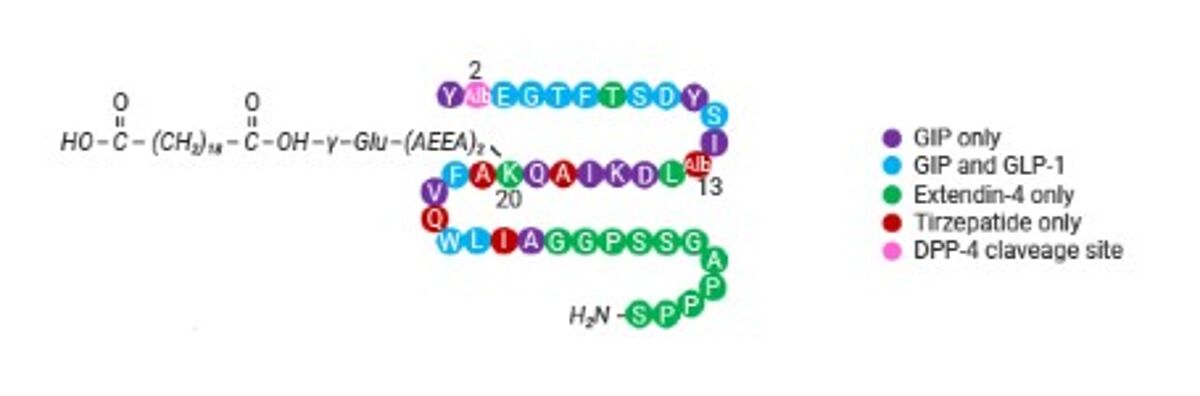
Tirzepatide is a dual GLP‑1R/GIPR agonist engineered based on incretins. It demonstrates superior efficacy over single‑target GLP‑1 RAs in glycemic and body weight management, and can be applied in T2D and obesity researches.
Tirzepatide is a 39-mer peptide engineered from GLP-1, GIP, and exenatide segments. Substitution with Aib at positions 2 and 13 results in DPP-4 resistance and increased stability. A C20 fatty di-acid moiety is added at Lys-20 for albumin binding, extending the half-life to five days (Figure 6) [9].
Retatrutide
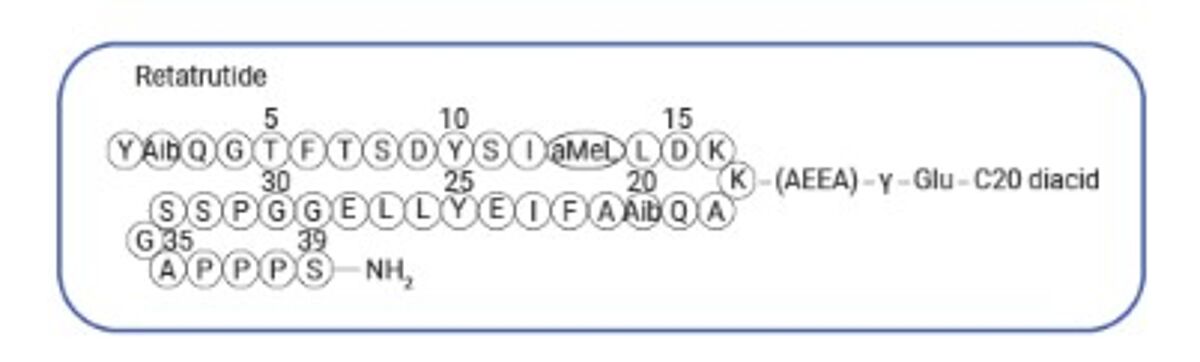
Retatrutide is a leading multi-receptor agonist candidate in phase III clinical development, activating GLP-1R, GIPR, and GCGR. By integrating multiple metabolic regulatory signals into a single peptide scaffold, retatrutide enables synergistic regulation of glucose homeostasis, body weight, and energy metabolism.
Structurally, retatrutide is based on a GIP/GLP-1 peptide scaffold incorporating key glucagon-derived residues, thereby conferring triple receptor agonism. Similar to semaglutide, retatrutide also incorporates Aib substitution and fatty acid conjugation to enhance metabolic stability and prolong its plasma half-life [10].
Amycretin
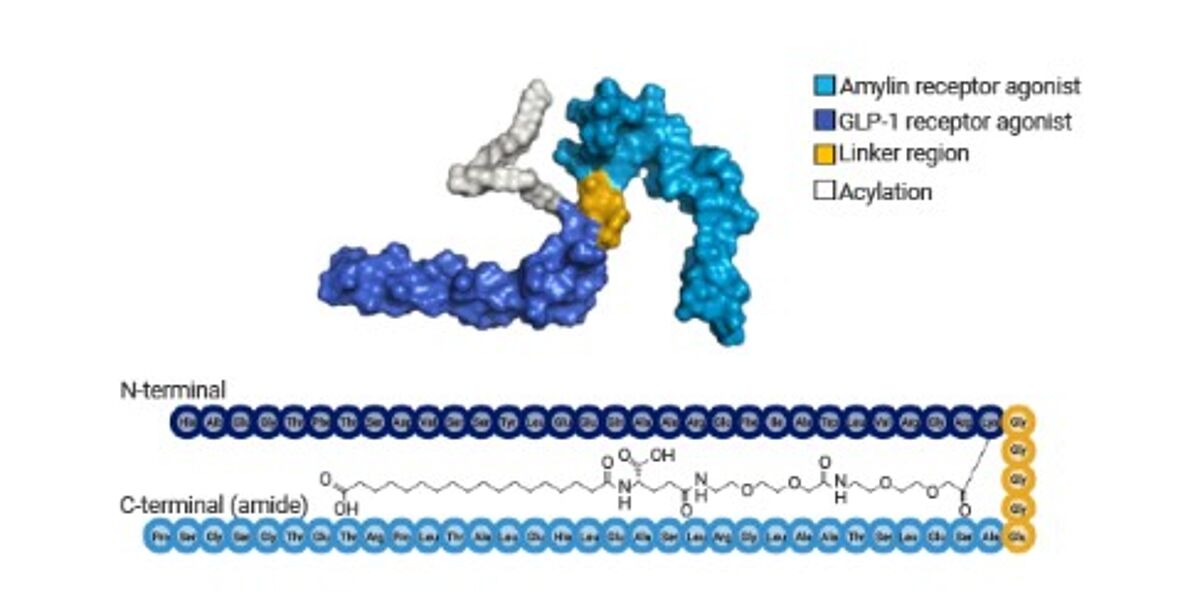
Amycretin is a rationally designed unimolecular dual receptor agonist derived from the amylin and GLP-1 scaffolds. By simultaneously activating GLP-1R and AMYR, it enables synergistic regulation of energy homeostasis and body weight, demonstrating remarkable weight-loss efficacy in clinical trials.
Amycretin consists of 68 amino acids and is formed by linking the GLP-1R agonist moiety and the AMYR agonist moiety via a linker peptide (GGGGE). The GLP-1R agonist moiety incorporates the unnatural amino acid Aib and long-chain fatty acid modifications to enhance stability and elongate the half-life (Figure 8) [11].
Summary
The sustained clinical success of GLP-1RAs in glycemic control and weight management has attracted increasing public attention and research investment in obesity and related metabolic diseases. This progress has also accelerated innovation in therapeutic targets, molecular design, and formulations, paving the way for next-generation obesity therapeutics.
MCE One-stop-service for obesity research
Al-driven drug discovery
MCE supports AI-driven drug discovery service that integrates molecular generation, structure prediction, virtual screening, and computational evaluation. These integrated capabilities enable efficient identification and optimization of candidates targeting key obesity-related pathways and therapeutic targets.
Custom peptide synthesis
MCE provides comprehensive custom peptide synthesis services to support obesity drug discovery and development, covering GLP-1 and multi-agonist peptide analogues, fatty-acylated peptides, long peptides, peptide–antibody conjugates (PACs), etc.
Drug screening service
A range of drug screening services is offered to support drug discovery and development, including GPCR screening (e.g., cAMP and β-arrestin assays for GLP-1R, GIPR, GCGR, and AMYR) and molecular interaction assays (SPR, MST, and ITC).
References
[1]. Glucagon-like peptide 1 in health and disease
[2]. Glucagon-like peptide 1(GLP-1) in biology and pathology
[5]. Dual and Triple Incretin-Based Co-agonists: Novel Therapeutics for Obesity and Diabetes
[6]. Amylin: emergent therapeutic opportunities in overweight, obesity and diabetes mellitus
[7]. Battle of GLP-1 delivery technologies
[8]. Daily Oral GLP-1 Receptor Agonist Orforglipron for Adults with Obesity

MCE - MedChemExpress
MedChemExpress offers high quality small molecules, reference compounds, APIs & natural compounds and inhibitor libraries. Supreme quality and rigorous QC testing by HNMR, LC-MS and HPLC - stability testing. Most compounds are tested for activity.